
Explore high, durable, and broad responses1-3

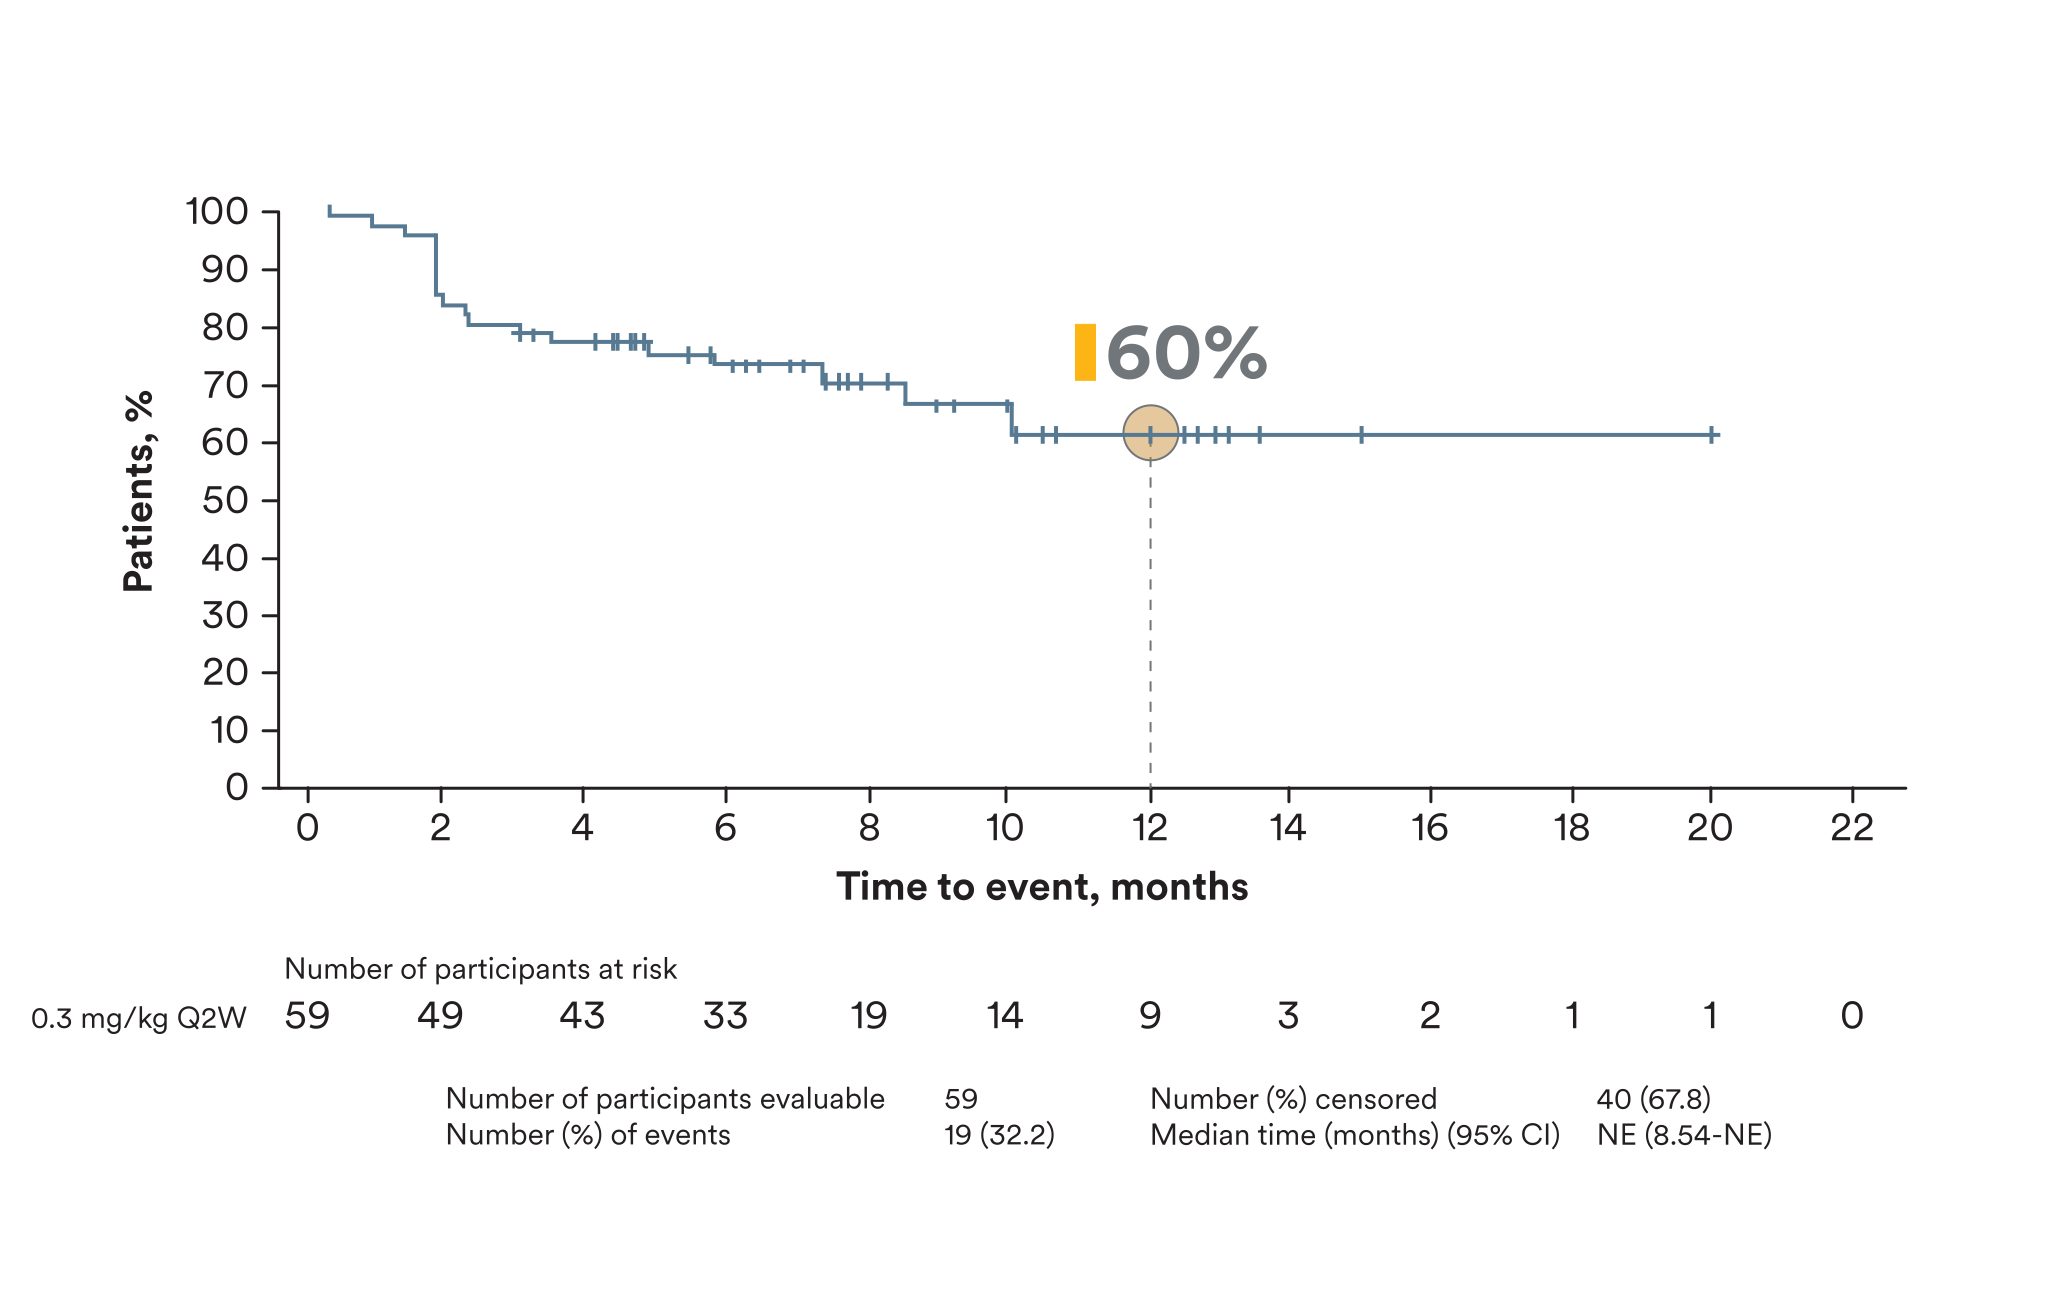
60% of patients maintained durable responses at 1 year1-3

Image

Swipe to view the
whole chart

Image
AGAVE-201 secondary endpoint: DOR1,3,a

Limitation: DOR was a prespecified secondary endpoint that was not powered for statistical significance and is therefore considered exploratory.8
Image
A line graph depicting duration of response, a secondary endpoint, in the AGAVE-201 trial. 59 patients in the 0.3 mg/kg Q2W dose group were evaluable and 60% of patients maintained a response at 12 months. 19 patients (32%) experienced an event. 40 patients, 68% of those evaluable, were censored at the last contact date, as they were still alive and hadn’t started new therapy. Median time was not evaluable, with a range from 8.54 months to not evaluable.
 

The median DOR, calculated from first response to progression, death, or new systemic therapies for cGVHD, was 1.9 months (95% CI, 1.6–3.5). In patients who achieved response, no death or new systemic therapy initiation occurred in 60% (95% CI, 43–74) of patients at 12 months since initial response1

aSensitivity analysis with DOR defined as the time from complete or partial response to start of new anti-GVHD systemic therapy or death from any cause, whichever was earlier. Patients who had not started new therapy and were still alive were censored at the last contact date.3

cGVHD=chronic graft-versus-host disease; CI=confidence interval; DOR=duration of response; NE=not evaluable; ORR=overall response rate; Q2W=every 2 weeks.

References: 1. Niktimvo Prescribing Information. Wilmington, DE: Incyte Corporation. 2. Wolff D, Cutler C, Lee SJ, et al; for the AGAVE-201 Investigators. Axatilimab in recurrent or refractory chronic graft-versus-host disease. N Engl J Med. 2024;391(11):1002-1014. Supplementary appendix available at: https://www.nejm.org/doi/full/10.1056/NEJMoa2401537. 3. Data on file. Incyte Corporation. Wilmington, DE. 4. Salhotra A, Bhatt V, Thomas B, Lou S, Radojcic V, DeFilipp Z. Axatilimab in patients with lung chronic graft-versus-host disease and related bronchiolitis obliterans syndrome: results from the AGAVE-201 study. Presented at: American Thoracic Society International Conference; May 17-21, 2025; San Francisco, CA. 5. Cutler C, Lee SJ, Arai S, et al; on behalf of the ROCKstar Study Investigators. Belumosudil for chronic graft-versus-host disease after 2 or more prior lines of therapy: the ROCKstar Study. Blood. 2021;138(22):2278-2289. 6. Choe H, Salhotra A, Farhadfar N, et al. Dynamics of overall and organ-specific responses to axatilimab in chronic graft-versus-host disease: analysis from the Agave-201 study. Blood. 2024;144(Supplement 1):98-99. 66th ASH Annual Meeting abstract 722. 7. Perez-Simon JA, DeFilipp Z, Lee S, et al. Axatilimab for chronic graft-versus-host disease: responses in fibrosis-dominant organs in AGAVE-201. Presented at: 50th Annual Meeting of the EBMT; April 14-17, 2024; Glasgow, Scotland. 8. A study of axatilimab at 3 different doses in participants with chronic graft versus host disease (cGVHD) (AGAVE-201). ClinicalTrials.gov. Updated June 16, 2026. Accessed June 16, 2026. https://clinicaltrials.gov/study/NCT04710576. 9. Wolff D, Cutler C, Lee SJ, et al. Safety and efficacy of axatilimab at 3 different doses in patients with chronic graft-versus-host disease (AGAVE-201). Presented at: 65th American Society of Hematology Annual Meeting and Exposition; December 9-12, 2023; San Diego, CA. 10. Teh C, Onstad L, Lee SJ. Reliability and validity of the modified 7-day Lee chronic graft-versus-host disease symptom scale. Biol Blood Marrow Transplant. 2020;26(3):562-567.

Examine the safety profile


IMPORTANT SAFETY INFORMATION

WARNINGS AND PRECAUTIONS

Infusion-Related Reactions

Niktimvo (axatilimab-csfr) can cause infusion-related reactions. Infusion-related reactions, including hypersensitivity reactions, occurred in 18% of patients who received Niktimvo in the clinical trial (AGAVE-201), with Grade 3 or 4 reactions in 1.3%.

INDICATIONS AND USAGE

Niktimvo (axatilimab-csfr) is a colony stimulating factor-1 receptor (CSF-1R)-blocking antibody indicated for the treatment of chronic graft-versus-host disease (cGVHD) after failure of at least two prior lines of systemic therapy in adult and pediatric patients weighing at least 40 kg.

Premedicate with an antihistamine and an antipyretic for patients who have previously experienced an infusion-related reaction to Niktimvo. Monitor patients for signs and symptoms of infusion-related reactions, including fever, chills, rash, flushing, dyspnea, and hypertension. Interrupt or slow the rate of infusion or permanently discontinue Niktimvo based on severity of the reaction.

Embryo-Fetal Toxicity

Based on its mechanism of action, Niktimvo may cause fetal harm when administered to a pregnant woman. Advise pregnant women of the potential risk to the fetus. Advise females of reproductive potential to use effective contraception during treatment with Niktimvo and for 30 days after the last dose.

ADVERSE REACTIONS

Serious adverse reactions occurred in 44% of patients who received Niktimvo (N=79). Serious adverse reactions in > 2 patients included infection (pathogen unspecified) (14%), viral infection (14%), and respiratory failure (5.1%). Permanent discontinuation of Niktimvo due to an adverse reaction occurred in 10% of patients and dose reduction due to adverse reaction occurred in 8% of patients. Dose interruptions due to an adverse reaction occurred in 44% of patients. The adverse reactions leading to dose interruption in > 2 patients were viral infection, infection (pathogen unspecified), bacterial infection, musculoskeletal pain, and pyrexia.

The most common (≥ 15%) adverse reactions, including laboratory abnormalities, were increased aspartate aminotransferase (AST), infection (pathogen unspecified), increased alanine aminotransferase (ALT), decreased phosphate, decreased hemoglobin, viral infection, increased gamma glutamyl transferase (GGT), musculoskeletal pain, increased lipase, fatigue, increased amylase, increased calcium, increased creatine phosphokinase (CPK), increased alkaline phosphatase (ALP), nausea, headache, diarrhea, cough, bacterial infection, pyrexia, and dyspnea.

Clinically relevant adverse reactions in < 10% of patients who received Niktimvo included:

  • Eye disorders: periorbital edema
  • Skin and subcutaneous skin disorders: pruritus
  • Vascular disorders: hypertension

Immunogenicity: Anti-Drug Antibody–Associated Adverse Reactions

Across treatment arms in patients with cGVHD who received Niktimvo in clinical trials, among the patients who developed anti-drug antibodies (ADAs), hypersensitivity reactions occurred in 26% (13/50) of patients with neutralizing antibodies (NAb) and in 4% (2/45) of those without NAb.

USE IN SPECIFIC POPULATIONS

Lactation

Because of the potential for serious adverse reactions in a breastfed child, advise women not to breastfeed during treatment and for 30 days after the last dose of Niktimvo.

Females and Males of Reproductive Potential

Pregnancy Testing

Verify pregnancy status in females of reproductive potential prior to initiating Niktimvo.

Contraception

Females
Advise females of reproductive potential to use effective contraception during treatment with Niktimvo and for 30 days after the last dose of Niktimvo.

DOSAGE AND ADMINISTRATION

Dosage Modifications for Adverse Reactions

Monitor aspartate aminotransferase (AST), alanine aminotransferase (ALT), alkaline phosphatase (ALP), creatine phosphokinase (CPK), amylase, and lipase prior to the start of Niktimvo therapy, every 2 weeks for the first month, and every 1 to 2 months thereafter until abnormalities are resolved. See Table 1 in the Prescribing Information for more recommendations.

Please see Full Prescribing Information for Niktimvo.